At a Glance:
Clear aligners and Invisalign® use removable trays to move teeth, but treatment systems can differ in materials, biomechanics, attachments, digital planning, and clinical monitoring. Invisalign® uses proprietary SmartTrack® material and can incorporate attachments, elastics, and other features to support planned tooth movements. Regardless of the aligner system, safe treatment depends on appropriate diagnosis, healthy supporting tissues, carefully planned forces, and monitoring of how the teeth and bite respond over time.
Clear aligners can look remarkably similar when viewed online: transparent trays shaped to fit over the teeth. That visual similarity can make clear aligners vs. Invisalign® seem like little more than a comparison between brands. Clinically, however, the differences can involve much more than the appearance of the tray.
Orthodontic tooth movement is a biological process. A tooth is supported within the jaw by the periodontal ligament and surrounding bone, and controlled forces applied to the tooth trigger changes in those supporting tissues.
How those forces are generated and managed depends on factors such as aligner material, tray design, attachments, treatment staging, the movements being attempted, and the patient’s individual anatomy.
For that reason, comparing clear-aligner systems requires looking beyond transparency, convenience, or branding. The more meaningful questions involve how the material behaves under sustained force, how the aligner creates different types of tooth movement, how the treatment plan creates space, and how clinicians assess whether the teeth, roots, bone, and bite are responding as intended.
Material Science: SmartTrack® vs. Other Clear Aligner Materials
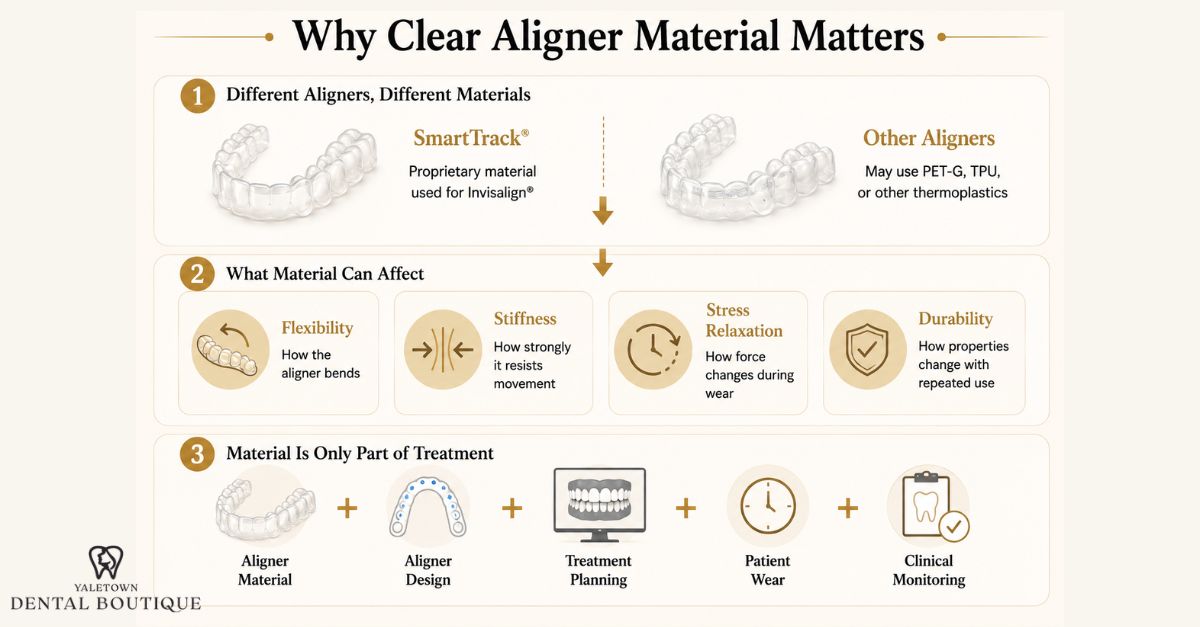
Clear aligners may look similar, but the polymers used to manufacture them can behave differently when exposed to body temperature, moisture, repeated insertion and removal, and sustained orthodontic loading. These properties can influence how an aligner fits, flexes, and delivers force during wear.
Invisalign® uses its proprietary SmartTrack® thermoplastic polymer, while other clear-aligner systems may use a range of materials, including polyethylene terephthalate glycol-modified (PET-G), thermoplastic polyurethane (TPU), polypropylene, polycarbonate, and multilayer polymer formulations, among others. Because materials and manufacturing methods vary between systems, “clear aligner plastic” is not a single standardized material.
Why does aligner material matter?
For an aligner to move teeth, it is designed with differences between the tooth’s current position and its planned position. When the aligner is seated, deformation of the material contributes to the forces and moments applied to the teeth.
Several material properties influence this behaviour:
- Elasticity: How a material responds and recovers after deformation
- Stiffness: How strongly the material resists deformation
- Stress relaxation: How stress within a material decreases while it remains under sustained deformation
- Creep: How a material gradually deforms under sustained loading
- Intraoral aging: How the oral environment and repeated wear can alter a material’s physical and mechanical properties
Research comparing clear-aligner materials has found differences in several of these properties, although translating laboratory measurements directly into clinical tooth-movement outcomes remains complex.

What is stress relaxation?
Stress relaxation is particularly relevant to clear-aligner materials. When an aligner is deformed as it seats over teeth that have not yet reached their planned positions, stresses develop within the polymer. While the material remains deformed, some of those stresses can decrease over time.
The amount and rate of stress relaxation vary according to factors such as polymer composition, manufacturing process, temperature and testing conditions. Studies therefore do not support assuming that every PET-G, polyurethane, or other aligner material follows the same force-decay pattern.
SmartTrack® vs. PET-G and Other Aligner Materials
The table below compares key characteristics of SmartTrack® with PET-G and other thermoplastics commonly used in clear aligner systems:
Comparing SmartTrack® With Other Clear Aligner Materials | ||
|---|---|---|
| Characteristic | SmartTrack® | PET-G & Other Thermoplastics |
| Material | Proprietary Multilayer Thermoplastic Polymer | PET-G, TPU, Polypropylene, Polycarbonate, or Other Formulations Depending on the System |
| Formulation | Developed Specifically for the Invisalign® System | Varies Considerably Among Manufacturers |
| Mechanical Behaviour | Designed to Provide Controlled Force Delivery During Invisalign® Treatment | Stiffness, Creep and Stress Relaxation Vary According to Material and Processing |
| Properties During Wear | Mechanical Properties Can Change with Intraoral Use | Properties Can Also Change with Thermoforming and Intraoral Aging |
| Treatment System | Integrated with Invisalign® Treatment Planning and Associated Clinical Features | Planning Systems and Clinical Protocols Vary by Manufacturer |
SmartTrack® should therefore not simply be compared with “generic plastic.” Different clear-aligner materials have measurable mechanical differences, but material alone does not determine the clinical result. Treatment staging, aligner geometry, attachments, tooth anatomy, patient wear, periodontal conditions and clinical monitoring can all influence how closely actual tooth movement follows the planned movement.
The Physics of Tooth Movement: Why Attachments and Buttons Matter
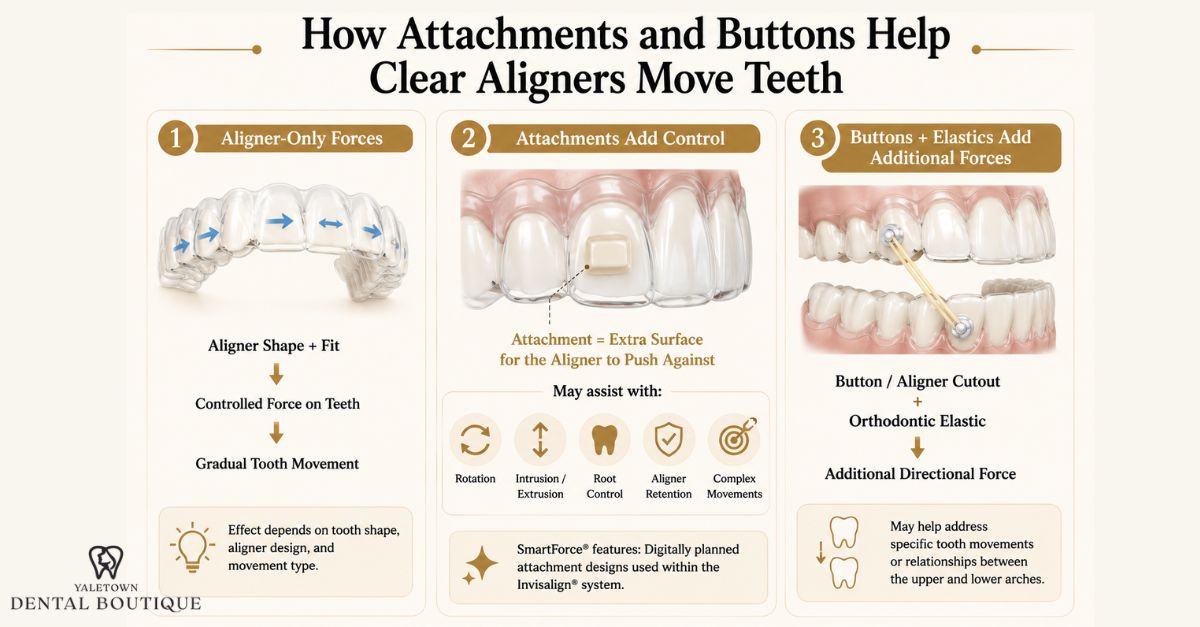
Clear aligners move teeth by applying controlled forces and moments through the tray. In simple terms, forces push or pull a tooth, while moments create a turning effect that helps control how the tooth rotates or tips. The way a tooth responds depends on where the force is applied, the shape of the tooth, aligner geometry, periodontal support, and the type of movement being attempted.
Some movements can be achieved through the shape and fit of the aligner alone. Others, such as certain rotations, intrusions, extrusions, or movements requiring greater root control, may benefit from attachments or other auxiliaries to improve how the force is delivered.
What do Invisalign® attachments do?
Attachments are small, tooth-coloured composite shapes bonded temporarily to selected teeth. They create additional surfaces for the aligner to engage, which can help modify the direction and magnitude of force applied to a tooth.
Depending on their design and position, attachments may assist with:
- Tooth rotation
- Intrusion or extrusion
- Root control
- Aligner retention
- More complex staged movements
Invisalign® refers to some of its digitally planned attachment designs as SmartForce® features. Align Technology describes these attachments as small bonded shapes that act like handles, giving the aligner additional surfaces to push against during treatment.
Why Smooth Aligners Have Mechanical Limits
A clear aligner contacts the visible crown of the tooth and can generate orthodontic forces without attachments. However, some movements are more difficult to control predictably because the tray may have limited ability to create the required force system on certain tooth shapes.
For example, rotational movement can be less predictable, particularly for teeth with rounded crown anatomy, and intrusion also shows variable predictability in clinical studies. Attachments and other auxiliaries may help improve control, but they do not guarantee that the planned movement will be fully achieved.
What are buttons and elastic cutouts?
Buttons are separate bonded auxiliaries that can be used with orthodontic elastics. Aligners may also contain cutouts or hooks that allow elastics to connect between the upper and lower arches.
These features can provide additional force when treatment requires correction of specific tooth movements or inter-arch relationships. Their use depends on the patient’s bite, treatment objectives, and clinical plan.
The key difference is the force system, not just the tray
The meaningful comparison is not simply aligners with attachments versus aligners without them.
Treatment success depends on the complete force system, including aligner geometry, attachment design, staging, tooth shape, periodontal support, patient wear, and clinical monitoring.
Digital treatment plans also do not always translate perfectly into actual tooth movement. Systematic reviews show that predictability varies considerably by movement type, which is why refinements, auxiliaries, and treatment adjustments may sometimes be required.
Biological Risks of Unsupervised Orthodontics: Root Resorption and Bone Loss
Clear aligners do more than reposition the visible crowns of teeth. Orthodontic movement depends on biological changes within the periodontal ligament (PDL) and alveolar bone surrounding each root. For that reason, the condition of the teeth, roots, gums, and supporting bone matters before and during treatment.
What Happens to the Bone When a Tooth Moves?
The periodontal ligament is a specialized connective tissue between the tooth root and its surrounding socket. When orthodontic force is applied, mechanical loading triggers cellular and molecular changes in the PDL and nearby bone.
In simplified terms:
- Osteoclasts participate in bone resorption where bone needs to be remodelled to allow tooth movement.
- Osteoblasts participate in new bone formation as the supporting tissues adapt.
- The periodontal ligament helps transmit mechanical forces and participates in the biological signalling that coordinates these changes.
This remodelling process allows teeth to move gradually through the alveolar bone.
Why Force Magnitude and Direction Matter
Orthodontic movement depends on more than simply applying greater force. The magnitude, direction, duration, and distribution of force can influence how the periodontal ligament and bone respond.
Excessive or poorly controlled loading may produce undesirable tissue responses rather than simply making teeth move faster. This is one reason orthodontic planning needs to consider root anatomy, bone support, periodontal health, and the specific movement being attempted.
What is orthodontically induced root resorption?
External apical root resorption is a recognized potential consequence of orthodontic tooth movement in which some root structure, most commonly near the root tip, is resorbed during treatment.
Small amounts may occur without noticeable symptoms and may only be identified on imaging.
More extensive resorption is less common, and susceptibility varies between individuals.
Factors that may influence risk include:
- Individual biological susceptibility
- Root shape and previous root condition
- Type and extent of tooth movement
- Treatment duration
- Previous dental trauma
- Characteristics of the orthodontic force system
Root resorption is not unique to Invisalign®, other clear aligners, or mail-order aligners. Several systematic reviews and meta-analyses have reported lower levels of external apical root resorption with clear aligners than with fixed appliances, although findings are not entirely consistent and the certainty of the evidence remains limited.
Why Bone and Gum Health Matter Before Moving Teeth
Orthodontic tooth movement occurs within the limits of the surrounding alveolar bone and periodontal tissues. Existing periodontal disease, inflammation, reduced bone support, or other dental conditions can influence treatment planning and risk.
A clinical examination and appropriate diagnostic records help determine whether the supporting tissues are suitable for orthodontic movement. Maintaining good oral hygiene is important during treatment, and professional oral hygiene guidance may also support daily plaque control when needed.
Where Unsupervised Treatment Creates Uncertainty
The concern with minimally supervised or remote orthodontic treatment is not that the aligners automatically damage roots or bone. The greater issue is that important biological or structural conditions may be missed when treatment is planned or continued without adequate clinical examination and diagnostic records.
Photographs, scans, and impressions can show tooth position, but they do not by themselves establish the condition of the roots, periodontal tissues, or supporting bone. Appropriate radiographic assessment may provide information that is not visible from the surface.
Monitoring also matters once treatment begins. Teeth do not always move exactly as predicted digitally, and changes in tracking, bite, periodontal health, or root position may require reassessment and treatment modification.
For this reason, discussions about mail-order aligners and root resorption are better framed around the importance of diagnosis and clinical monitoring rather than implying that a particular delivery model inevitably causes root damage.
Managing the Bite: Monitoring for a Posterior Open Bite
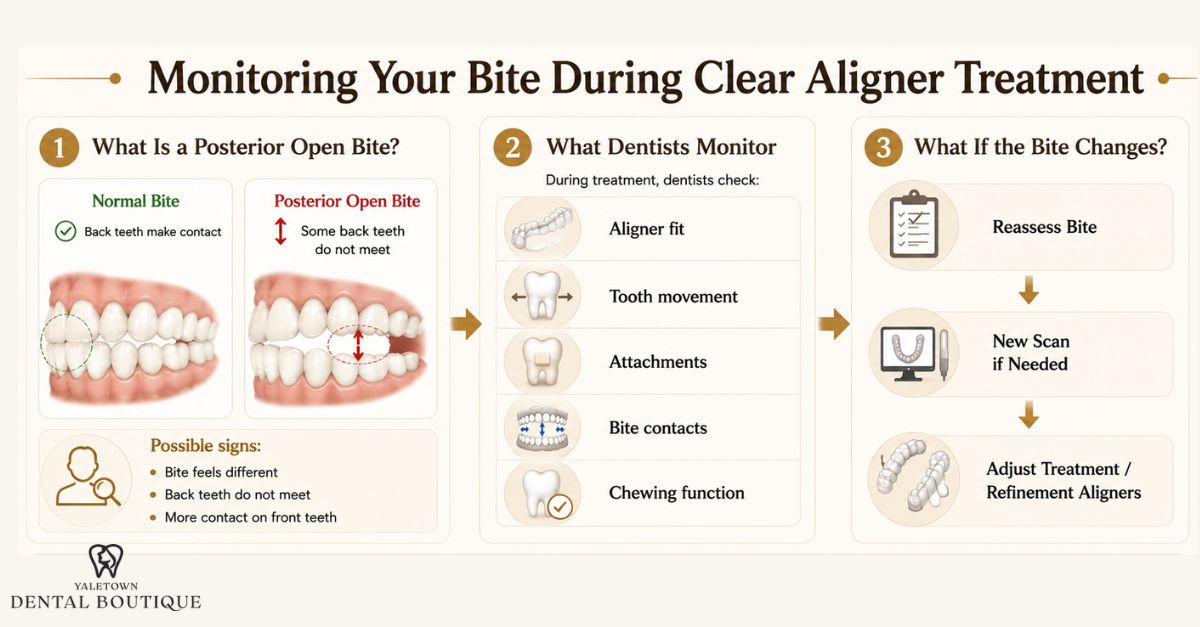
Straightening the visible teeth is only one part of clear aligner treatment. Dentists also monitor how the upper and lower teeth contact as treatment progresses.
One bite change that can occur during clear aligner therapy is a posterior open bite, where some of the back teeth no longer make the expected contact when the patient bites together.
What is a posterior open bite?
Normally, the upper and lower back teeth contact in a coordinated way during biting and chewing.
With a posterior open bite, contact between one or more posterior teeth is reduced or absent even though other teeth may meet normally.
A patient may notice:
- Difficulty bringing the back teeth together
- A sensation that the bite has changed
- More contact on the front teeth than before
- Reduced chewing contact on certain back teeth
These symptoms are not specific to one cause, so the bite needs to be assessed clinically.
Why can posterior open bite develop during clear aligner treatment?
Clear aligners cover the chewing surfaces of the teeth while they are worn, and treatment simultaneously changes the positions of teeth throughout the arches. As a result, the developing bite can be influenced by the planned tooth movements, actual biological response, aligner fit, and changes in occlusal contact during treatment.
Posterior open bite may be associated with factors such as unintended vertical tooth movement, differences between planned and achieved movement, or an imbalance in how the anterior and posterior teeth settle during treatment.
Research on vertical tooth movement with clear aligners is mixed. Some studies report posterior intrusion, while others find that changes in overbite are driven primarily by anterior tooth movement. The mechanism therefore cannot be reduced to the aligner material simply “pushing the molars down.”
Why Tracking Matters
The digital setup represents the planned sequence of tooth movements, but actual tooth movement does not always reproduce the digital prediction exactly.
A tooth is considered to be tracking when its clinical position remains reasonably consistent with the aligner and intended treatment stage. A visible gap between the aligner and tooth, altered bite contacts, or changes in fit may indicate that reassessment is appropriate.
Clinical reviews can evaluate:
- Tooth position and movement
- Aligner fit and seating
- Attachment integrity
- Periodontal health
- Developing bite contacts
- Changes in chewing function
What Happens If the Bite Is Not Developing as Planned?
Management depends on the cause and stage of treatment. A dentist may reassess tooth positions and bite contacts, obtain a new digital scan, modify the remaining treatment plan, or prescribe refinement aligners based on the updated anatomy.
In Invisalign® treatment, these changes can be incorporated into a revised digital treatment setup. Other clear-aligner systems may use different refinement workflows.
Additional orthodontic features or auxiliaries may also be considered depending on the specific bite problem.
A posterior open bite during clear aligner treatment does not automatically mean treatment has failed. It is a clinical finding that should be evaluated in context so the treatment plan can be adjusted when appropriate.
In-Office Diagnostics: Interproximal Reduction (IPR) vs. Arch Expansion
Crowded teeth need enough space to move into their planned positions. In clear aligner treatment, that space may come from several strategies, including interproximal reduction (IPR), dentoalveolar expansion, use of existing space, or extraction in selected cases.
The appropriate approach depends on factors such as the amount and location of crowding, tooth size, arch form, bite relationship, periodontal support, and the position of the teeth within the supporting bone.
What is interproximal reduction (IPR)?
Interproximal reduction, or IPR, involves removing a small, controlled amount of enamel from the contact surfaces between selected teeth.
The goal is to create modest amounts of space that can be used for alignment or to help manage tooth-size discrepancies. IPR is commonly planned in small fractions of a millimetre, with the amount determined according to the tooth anatomy and treatment objectives.
IPR may be used to:
- Create space for mild or moderate crowding
- Help manage tooth-size discrepancies
- Assist with selected alignment goals
- Modify interproximal contacts
- Reduce the amount of expansion or other tooth movement required in appropriate cases
Because enamel removal is irreversible, the location and amount of IPR should be planned conservatively and based on the individual clinical situation.
How is IPR performed?
When indicated, a dental professional uses controlled instruments to reduce a prescribed amount of enamel between selected teeth. Techniques may involve abrasive strips, discs, or other dedicated interproximal reduction instruments.
The amount removed is checked clinically, and the treated surfaces may then be finished and polished.
Clinical studies and systematic reviews generally suggest that appropriately performed IPR can be used without clear evidence of increased caries or periodontal harm, although the overall quality of the evidence is limited and longer-term studies are still needed.
What does arch expansion mean?
In clear aligner treatment, arch expansion usually refers to increasing dental arch width by repositioning teeth outward.
In adults, this is primarily a dentoalveolar movement, meaning the change occurs through tooth movement and changes in tooth inclination within the supporting tissues rather than predictable skeletal widening of the jaw. Systematic reviews of Invisalign® expansion have found that much of the transverse change is associated with buccal crown tipping.
Expansion also has biological limits. The position of the roots, the available alveolar bone, and periodontal health need to be considered when planning how far teeth can reasonably be moved.
IPR vs. Expansion: How are they different?
Here’s how IPR and dentoalveolar expansion differ in the way they create space and the factors that guide their use:
IPR vs. Dentoalveolar Expansion in Clear Aligner Treatment | ||
|---|---|---|
| Factor | Interproximal Reduction (IPR) | Dentoalveolar Expansion |
| How Space Is Created | Small Amounts of Enamel Are Removed Between Selected Teeth | Teeth Are Repositioned Outward to Modify Dental Arch Width |
| Typical Scale | Small Fractions of a Millimetre at Selected Contacts | Depends on the Planned Tooth Movements and Individual Anatomy |
| Changes Enamel? | Yes, in a Controlled Amount | No Enamel Removal Is Inherent to Expansion |
| Main Limitation | Available Enamel and Appropriate Indication | Supporting Bone, Periodontal Tissues, Tooth Inclination, and Movement Predictability |
| Planning Factors | Tooth Dimensions, Contacts, Enamel Availability, and Required Space | Arch Form, Root Position, Bone Support, Bite, and Amount of Planned Expansion |
These approaches are not mutually exclusive. Some treatment plans use both limited IPR and controlled dentoalveolar expansion, along with other movements, to create and distribute the space required for alignment.
Why the Clinical Examination Matters
A digital treatment simulation can help estimate how much space is needed and where it may be created, but it does not replace assessment of the patient’s actual teeth, roots, gums, bite, and supporting bone.
The clinician may consider tooth dimensions, enamel availability, periodontal health, crowding severity, arch form, root position, and the relationship between the upper and lower teeth before deciding which space-creating strategy is appropriate.
Digital scans are useful for documenting tooth positions and developing or revising the aligner setup. If actual movement differs from the planned sequence, a new scan and treatment refinement may be considered.
Conclusion
The difference between clear aligners and Invisalign® goes beyond how the trays look. Aligner material, force delivery, attachments, treatment staging, space creation, and the biological response of the teeth and supporting tissues can all influence how treatment progresses.
Clear aligner treatment is also not entirely predictable from a digital simulation. Teeth may track differently than planned, bite relationships can change, and factors such as periodontal health, root position, and available bone need to be considered throughout treatment. Clinical assessment and monitoring help identify these changes and determine when refinements or other adjustments may be appropriate.
Ultimately, clear aligners vs. Invisalign® is not simply a comparison of two types of plastic trays. It is a comparison of treatment systems, biomechanics, materials, diagnostic processes, and clinical workflows. The appropriate approach depends on your tooth positions, bite, supporting tissues, and individual treatment goals.
Can generic clear aligners fix a severe overbite or underbite?
Some clear aligners can manage more complex bite problems, but suitability depends on the severity and type of malocclusion. Complex cases may require attachments, elastics, other orthodontic appliances, or a different treatment approach.
What happens if a tooth stops tracking during clear aligner treatment?
If a tooth no longer follows its planned movement, the clinician may assess the aligner fit and attachments, obtain a new digital scan, or use refinement aligners to modify the treatment plan.
Why do my Invisalign® aligners have small bumps or cutouts?
Raised areas may correspond with attachments that help control specific tooth movements. Cutouts may also accommodate buttons or elastics used for certain movements or bite corrections.
Can mild tooth mobility occur during aligner therapy?
A small increase in mobility can occur as the periodontal ligament and surrounding bone remodel during orthodontic movement. Noticeable or increasing looseness, especially with significant pain, swelling, or dental trauma, should be assessed promptly. Symptoms that may require emergency intervention should not be assumed to be a routine part of aligner treatment.
Can I switch from a mail-order aligner system to Invisalign® mid-treatment?
Potentially. A dentist would first need to assess your current tooth positions, bite, periodontal health, and previous treatment. New scans and a revised treatment plan may be required.
Why don’t my back teeth touch after clear aligner treatment?
Reduced contact between the back teeth can sometimes develop during clear aligner treatment and may represent a posterior open bite. The cause should be assessed because management depends on the specific tooth movements and bite relationship.